
Clinical Cases Comparison
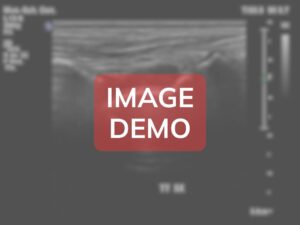
AN-ANT-SE-A1099 - Severe
VS
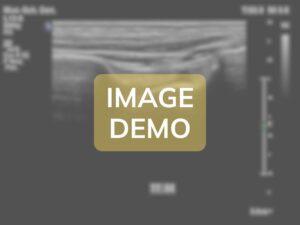
AN-ANT-MI-A1097 - Mild



Diagnosis
AN-ANT-SE-A1099
This case represents end-stage hemophilic ankle arthropathy with score of 14/16 indicating near-maximal structural damage and profound disability. The extensive destruction reflects decades of inadequate hemostatic control, compounded by non-adherence during young adulthood. Current management focuses on palliation: maximal prophylaxis primarily prevents further bleeding rather than reversing damage. Pain management requires multimodal approach including long-acting opioids, gabapentin, duloxetine, and topical therapies, though control remains suboptimal (VAS 6-7/10). Ankle arthrodesis remains definitive surgical option but presents significant challenges: perioperative bleeding risk, poor bone quality with extensive erosions, severe soft tissue contracture, infection risk, and uncertain functional outcome. Patient has elected to defer surgery, preferring conservative management. Physical therapy focuses on maintenance goals: preserving residual motion, slowing atrophy, aquatic therapy, and gait training with bilateral crutches and custom AFO. Psychosocial support addresses severe depression and functional limitations through CBT, support groups, and vocational rehabilitation. Prognosis is poor for functional improvement without surgery, though even successful arthrodesis will leave permanent severe limitation. This case exemplifies devastating consequences of inadequately treated hemophilia and underscores the critical importance of early prophylaxis in preventing such catastrophic outcomes in modern hemophilia care.
AN-ANT-MI-A1097
This case represents early-stage hemophilic arthropathy of the ankle with mild alterations detected on ultrasound that are subclinical or minimally symptomatic. The score indicates minimal structural damage with excellent potential for stabilization or reversal with optimal hemostatic management. The patient's late start of prophylaxis (age 45) likely contributed to development of these early changes, highlighting the importance of early prophylaxis initiation to prevent joint damage. However, the relatively mild presentation despite decades without prophylaxis may reflect his moderate rather than severe hemophilia phenotype. Current management includes continuation of prophylaxis with consideration of increasing frequency to three times weekly if breakthrough bleeding occurs. Physical therapy has been prescribed focusing on ankle proprioception, dorsiflexion range of motion exercises, and gastrocnemius-soleus stretching to address the mild restriction. Patient education emphasizes activity modification to avoid high-impact activities and twisting motions that could provoke hemorrhage. Close monitoring with repeat ultrasound in 6-8 months is recommended to assess for progression versus stabilization of the synovial and cartilage changes. The prognosis is good with appropriate prophylaxis adherence and joint protection strategies. This case demonstrates the value of ultrasound in detecting early subclinical joint changes before significant functional impairment develops, allowing for intervention at a stage where disease modification may still be possible.
VS
Anatomical Zone
VS